


Pharmacy technicians have been on the ARRS list since April 2020. The number of practices that deploy one well is smaller than the number with one on the books. The role description sounds administrative. The good ones are not.
This piece sets out what a technician is, what they can run independently, where they free up pharmacist and GP time, and the deployment patterns that turn the role into a glorified prescription clerk.
What a technician is and is not
A pharmacy technician registered with the GPhC has completed a level 3 qualification, two years of pre-registration practice, and ongoing CPD. They are clinically qualified. They are not pharmacists. They can support medicines reviews within their assessed competence and agreed scope. Clinical assessment and prescribing decisions require appropriately qualified clinicians.
What they can do, with appropriate training and supervision, is run the operational layer of medicines management. Repeat prescription processing. Hospital discharge reconciliation. Audit data extraction. Patient contact about routine medicines issues. Specific medication-related clinics under protocol.
What technicians can run independently
Six pieces of work move cleanly to a technician.
Repeat prescription processing. Preparing routine repeat requests against agreed criteria for authorisation by an appropriately qualified prescriber. Identifying patients due for review and routing them to the pharmacist or GP. Removing items no longer prescribed.
Hospital discharge reconciliation. Checking discharge letters against existing prescriptions. Identifying changes. Flagging clinically significant changes to the pharmacist. Updating prescribing records.
High-risk drug monitoring administration. Sending bloods reminders. Generating phlebotomy forms. Following up missed appointments. Updating the practice register.
Compliance and dosette work. Liaising with community pharmacy on dosette supply. Identifying patients who would benefit from compliance aids. Handling the paperwork.
Specific audit work. Pulling lists for prescribing audits. Cross-referencing prescribing data against guidelines. Producing audit reports.
Patient contact for routine queries. Handling questions about generic switches, supply problems, repeat ordering and hospital prescriptions within assessed competence and the agreed scope. Taking details of suspected side effects and referring concerns that need clinical assessment to the pharmacist or another appropriate clinician.
Where technicians free up pharmacist time
The unspoken rule of clinical pharmacist deployment in general practice is that the pharmacist’s time is worth most when they are doing prescribing-level clinical work. Every hour of pharmacist time spent on repeat authorisation or discharge reconciliation is an hour not spent on medication review or high-risk drug management.
A technician absorbs the operational layer. A technician can release pharmacist time for clinical contacts by taking on agreed operational tasks. The effect depends on the scope, workload, competence and supervision arrangements.
The appropriate mix of pharmacists and technicians depends on the network’s workload, skills and supervision capacity. Define the work first, then agree the balance of roles.
The deployment mistakes
Technician hired with no protected supervision. The role needs a named clinical supervisor (a pharmacist or senior pharmacist) and protected time for the supervision to happen. Practices that skip this end up with a technician working blind on tasks that need clinical oversight.
Technician used as a general admin. Front-line phone work. Booking appointments. Scanning. Filing. The role goes the way of any other administrative role and the medicines work it was meant to absorb stays with the pharmacist.
No agreed scope of practice. Without a written scope and escalation route, routine tasks can create avoidable queries for the supervising clinician. The scope should distinguish administrative processing from clinical and prescribing decisions.
Hired the wrong band. A technician straight out of training cannot run the operational layer of a busy practice without daily supervision. A senior accuracy-checking technician with five years of clinical pharmacy experience can.
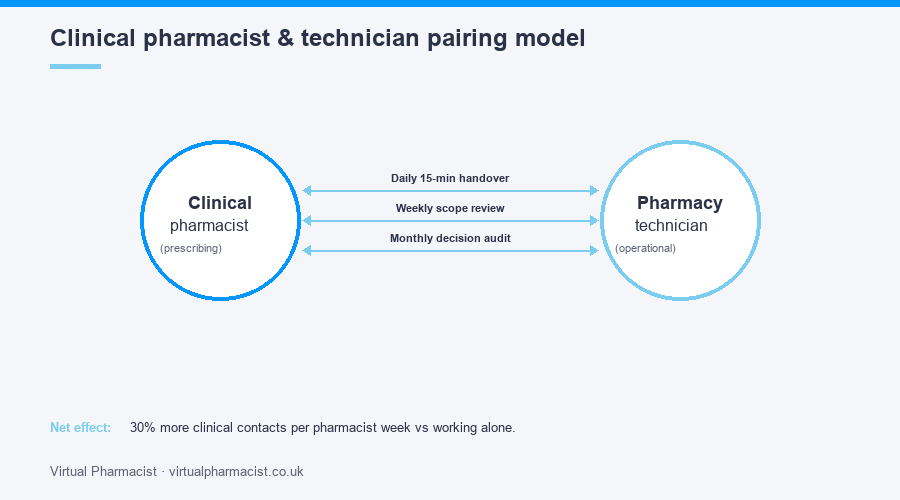
Pairing technicians with pharmacists
The pairing model that works is straightforward.
Daily quick-fire handover, 15 minutes. What the technician picked up. What needs clinical input. What the pharmacist is working on. What is parked.
Weekly review of the agreed scope. Has anything new come up that needs to be added to the scope or escalated out of it?
Monthly audit of decisions. A sample of decisions the technician made. The pharmacist reviews for clinical safety. Adjustments to scope follow.
This pattern keeps the technician growing in scope without the pharmacist needing to supervise every individual decision.
Getting the role right
The practices and PCNs that get the most from their technician role tend to do three things on day one.
Write the scope of practice as a one-page document and put it on the technician’s desk. Update it quarterly.
Pair the technician with a named pharmacist supervisor, not a rotating group. Continuity of supervision matters more than the supervisor’s grade.
Track the work. Number of repeat requests processed within the agreed scope. Number of discharge reconciliations. Number of audits completed. The data is what justifies the role to GP partners.
Our fully managed pharmacy technician support service covers the work, its supervision and clinical oversight under a single contract. Get in touch for a deployment review.
Frequently asked questions
What can a pharmacy technician do independently in a GP practice?
With a written scope and named supervision, a technician can run repeat prescription processing, hospital discharge reconciliation, high-risk drug monitoring administration, compliance aid liaison, audit data extraction, and routine patient medicines queries.
Can a pharmacy technician carry out medication reviews?
Clinical medication reviews are carried out by appropriately trained clinicians, and prescribing decisions require an authorised prescriber. Pharmacy technicians support records, medicines reconciliation and follow-up within their competence and agreed scope.
What ratio of technicians to pharmacists works best?
The appropriate mix of pharmacists and technicians depends on the network's workload, skills and supervision capacity. The pairing matters more than the exact ratio, together with a named supervisor and a one-page scope of practice reviewed quarterly.
What stops the role working?
Four deployment mistakes account for most of it: no protected supervision time, the technician absorbed into general admin, no written scope so every decision returns to the pharmacist, and hiring at a band too junior for the operational load.





